
Colorectal Cancer: A Clear Guide to Diagnosis, Staging and Treatment
Colorectal cancer is cancer that begins in the colon or rectum. Understanding colorectal cancer diagnosis, staging and treatment can make an overwhelming diagnosis easier to navigate — from the first colonoscopy and pathology report to decisions about surgery, chemotherapy, immunotherapy and follow-up care.
This guide explains what the major tests mean, how doctors determine the stage of colorectal cancer, why colon and rectal cancer are sometimes treated differently, and how treatment decisions change when cancer has spread.
Colorectal cancer diagnosis and treatment are supported by extensive clinical research and established oncology guidelines. Surgery, systemic treatments, radiotherapy and selected local treatments can be highly effective when matched to the cancer’s stage, location and molecular characteristics.
There is no single treatment plan that is right for every patient.
THE SHORT ANSWER
Colorectal cancer is not one uniform disease. Two people may have tumors in the same organ but need different treatments because their cancers differ in stage, location, genetic characteristics and extent of spread.
Doctors usually need to answer five questions:
- Where exactly did the cancer begin?
- How far has it grown into the bowel wall?
- Has it reached nearby lymph nodes?
- Has it spread to distant organs?
- What molecular characteristics could influence treatment?
These answers shape the treatment plan and help determine whether the main goal is cure, long-term disease control or symptom relief.
WHAT IS COLORECTAL CANCER?
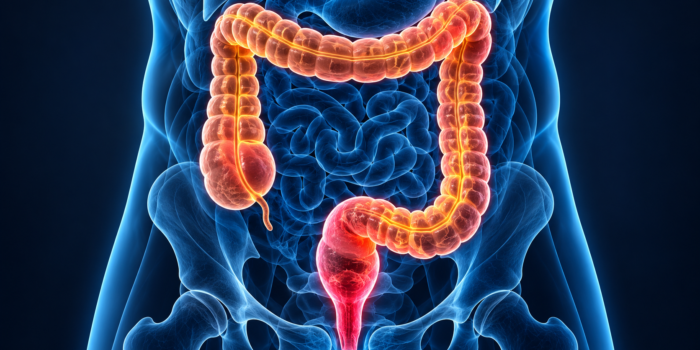
The colon and rectum form the final portions of the digestive tract. The colon absorbs water and helps form stool. The rectum stores stool before it leaves the body.
Most colorectal cancers are adenocarcinomas, which develop from gland-forming cells in the intestinal lining.
Many begin as precancerous growths called polyps. Certain polyps can accumulate genetic changes over time and eventually develop into invasive cancer.
Colon cancer begins in the large intestine above the rectum.
Rectal cancer begins in the rectum, close to the anus.
The distinction matters because rectal tumors sit within the pelvis, where surgical anatomy and the risk of local recurrence often make pelvic MRI, radiotherapy and treatment before surgery particularly important.
SYMPTOMS AND WARNING SIGNS
Early colorectal cancer may cause no symptoms. When symptoms occur, they can include:
- Blood in the stool or rectal bleeding
- A persistent change in bowel habits
- Unexplained iron-deficiency anemia
- Abdominal pain or persistent discomfort
- Unexplained weight loss
- A feeling that the bowel does not empty completely
- Fatigue, sometimes related to anemia
These symptoms can also have noncancerous causes, including hemorrhoids, infections and inflammatory bowel conditions. But persistent or unexplained symptoms deserve medical assessment.
Severe abdominal pain with vomiting and inability to pass stool or gas may indicate bowel obstruction. Heavy rectal bleeding, fainting or marked weakness also requires urgent medical attention.
RISK FACTORS AND SCREENING
Risk generally increases with age, but colorectal cancer can also occur in younger adults.
Important risk factors include:
- A personal history of colorectal polyps or cancer
- Family history of colorectal cancer
- Inherited syndromes such as Lynch syndrome or familial adenomatous polyposis
- Long-standing inflammatory bowel disease
- Smoking and heavy alcohol consumption
- Excess body weight and physical inactivity
- Dietary patterns associated with increased colorectal cancer risk
Screening can detect some cancers early and can also prevent cancer by finding and removing precancerous polyps.
Screening methods include colonoscopy, fecal immunochemical testing (FIT), stool DNA-based testing and other validated approaches.
In the United States, routine screening for adults at average risk commonly begins at age 45. Recommendations differ by country, and people with increased risk may need screening earlier.
Screening is intended for people without symptoms. Someone with persistent rectal bleeding, unexplained anemia or other concerning symptoms may need diagnostic evaluation regardless of age or routine screening eligibility.
A positive stool-based screening test generally requires a follow-up colonoscopy.
HOW COLORECTAL CANCER IS DIAGNOSED
1. Colonoscopy and biopsy
Colonoscopy allows a doctor to inspect the inside of the colon and rectum using a flexible camera.
If a suspicious lesion is found, tissue can be removed and examined by a pathologist.
The pathology examination is usually what confirms the cancer diagnosis.
2. Pathology
A pathology report may describe the tumor type, grade, depth of invasion, lymph-node involvement and other characteristics.
After surgery, the report can also show whether the surgical margins are free of cancer and whether lymphatic, vascular or nerve invasion is present.
3. Imaging
CT scans of the chest, abdomen and pelvis are commonly used to look for distant spread.
For rectal cancer, pelvic MRI is particularly important for assessing local tumor extent and planning treatment.
Liver MRI may be useful when CT identifies uncertain liver lesions or when detailed assessment is needed before liver surgery.
PET/CT is not required routinely for every patient. It may be considered when a specific unresolved clinical question could affect management.
4. Blood tests
Blood tests can evaluate anemia, liver function, kidney function and general treatment readiness.
Doctors may also measure carcinoembryonic antigen, or CEA, as a baseline tumor marker.
CEA is useful in some patients for monitoring, but it cannot reliably diagnose or exclude colorectal cancer on its own.
UNDERSTANDING THE TNM STAGING SYSTEM
Colorectal cancer staging describes how far the disease has spread.
The TNM system evaluates three separate components:
T — Tumor: How deeply the primary cancer has grown into or through the bowel wall and surrounding structures.
N — Nodes: Whether cancer has reached nearby regional lymph nodes.
M — Metastasis: Whether cancer has spread to distant organs or tissues.
For example, T4a indicates that the tumor has penetrated the visceral peritoneal surface. N2a indicates involvement of four to six regional lymph nodes. M1 indicates distant metastatic disease.
A patient’s stage may be assessed clinically before treatment and pathologically after surgery. These assessments are not always identical.
COLORECTAL CANCER STAGES 0–IV
Abnormal cancerous cells remain within the innermost lining without invasion into deeper tissue. Local removal is generally sufficient when completely excised.
The tumor has invaded deeper layers of the bowel wall but has not spread to regional lymph nodes or distant organs. Surgery is usually the main treatment.
The tumor has grown through deeper bowel-wall layers or into nearby structures, but regional lymph nodes are negative. Surgery is the main treatment for colon cancer; additional therapy depends on risk factors and molecular findings.
Cancer has spread to regional lymph nodes but not to distant organs. Surgery and chemotherapy are commonly used for colon cancer. Rectal cancer often requires a different sequence of treatments.
Cancer has spread to distant sites, such as the liver, lungs, distant lymph nodes or peritoneum. Treatment depends on the distribution of disease, molecular findings and whether all known sites can be treated locally.
Stage III and Stage IV are not interchangeable. Positive regional lymph nodes do not automatically mean distant metastatic disease.
Likewise, a Stage IV diagnosis does not by itself establish whether a potentially curative treatment strategy is possible.
WHAT DO R0, R1 AND R2 MEAN?
After surgery, the surgical team and pathologist may describe the completeness of tumor removal using the R classification.
- R0: No residual tumor identified at the assessed resection margins.
- R1: Microscopic residual tumor at a resection margin.
- R2: Macroscopic residual tumor remains.
An R0 resection is an important favorable surgical result.
However, R0 does not prove that no microscopic cancer cells exist anywhere in the body. It describes the resection status, not a guarantee against recurrence.
HOW STAGE I AND II COLON CANCER ARE TREATED
For many patients with Stage I colon cancer, complete surgery is sufficient.
Stage II colon cancer is also primarily treated with surgery, but the decision about additional chemotherapy is more individualized.
Factors that may influence that discussion include:
- T4 tumor invasion
- Bowel obstruction or perforation
- Inadequate lymph-node sampling
- High-risk pathological features
- Mismatch repair or microsatellite instability status
- Overall health and treatment preferences
Adjuvant chemotherapy is not automatically necessary for every patient with Stage II disease.
In particular, dMMR/MSI-H status can change the expected benefit of certain chemotherapy approaches.
HOW STAGE III COLON CANCER IS TREATED
Stage III colon cancer usually involves surgical removal of the primary tumor and regional lymph nodes, followed by consideration of adjuvant chemotherapy.
Common chemotherapy regimens include:
- FOLFOX: Fluorouracil, leucovorin and oxaliplatin.
- CAPOX: Capecitabine and oxaliplatin.
These treatments aim to eliminate microscopic cancer cells that may remain after surgery and reduce the risk of recurrence.
The duration of treatment is individualized according to recurrence risk, the regimen used and potential side effects.
Oxaliplatin can cause peripheral neuropathy, including numbness, tingling and cold sensitivity. The potential benefit of additional treatment must be balanced against the risk of persistent nerve damage.
WHY RECTAL CANCER IS OFTEN TREATED DIFFERENTLY
Rectal cancer treatment requires special attention to the pelvis, surrounding organs and the possibility of preserving bowel function.
For many patients with locally advanced rectal cancer, treatment is given before surgery.
This may include chemotherapy, radiotherapy or a combination known as total neoadjuvant therapy (TNT).
Some carefully selected patients may receive chemotherapy without routine pelvic radiotherapy, while others benefit from chemoradiation.
For certain rectal cancers with dMMR/MSI-H biology, immunotherapy has become an important specialized treatment consideration.
In patients who achieve a complete clinical response after neoadjuvant treatment, expert teams may consider a nonoperative watch-and-wait approach with intensive surveillance.
Nonoperative management of rectal cancer is reserved for carefully selected patients after a documented clinical response. It requires specialized assessment and rigorous follow-up because local regrowth can occur.
STAGE IV: WHEN COLORECTAL CANCER HAS SPREAD
Stage IV colorectal cancer means the disease has spread beyond the primary site and regional lymph nodes.
The most common distant sites include the liver and lungs. The peritoneum and distant lymph nodes can also be involved.
But Stage IV disease includes very different clinical situations.
A patient with two treatable liver metastases may have a fundamentally different treatment strategy from someone with extensive disease in several organs.
Curative intent: Treatment is designed to eliminate all known disease with a realistic possibility of long-term freedom from cancer. This may involve surgery, ablation and systemic therapy.
Disease control: Treatment is intended primarily to shrink or stabilize cancer, extend survival, reduce symptoms and preserve quality of life when eradication of all disease is not currently feasible.
The distinction depends on individual clinical findings, not the stage number alone.
LIVER METASTASES: CAN THEY BE TREATED?
Yes. The liver is one of the most important areas of treatment for metastatic colorectal cancer.
When metastases are limited and can be completely treated, surgery may offer a possibility of long-term disease-free survival and, in selected patients, cure.
Whether liver metastases can be removed depends on more than their number.
Surgeons evaluate:
- The size and location of lesions
- Proximity to major blood vessels and bile ducts
- Whether sufficient functioning liver can remain
- The presence or absence of disease outside the liver
- The biological behavior of the cancer
- Response to systemic treatment
In some patients, chemotherapy can shrink previously unresectable disease enough to make surgery possible.
What about ablation?
Ablation destroys tumor tissue using heat or another local energy source.
Techniques include microwave ablation and radiofrequency ablation.
Ablation may be considered for selected small lesions, especially when surgery is difficult or when it can complement a surgical approach.
Location matters. Lesions near major bile ducts or sensitive structures may require additional precautions or alternative approaches.
What about liver transplantation?
Liver transplantation is being used or studied for highly selected patients with unresectable colorectal liver metastases under strict criteria at specialized centers.
It is not a routine option for most patients with metastatic colorectal cancer.
Potentially treatable liver metastases should ideally be reviewed by a multidisciplinary team that includes an experienced hepatobiliary surgeon, medical oncologist, radiologist and interventional specialist.
A lesion initially described as unresectable does not always remain unresectable after further treatment or specialist review.
WHAT ABOUT LUNG METASTASES?
Selected patients with a limited number of lung metastases may also be candidates for local treatment.
Depending on the situation, options can include surgical removal, stereotactic radiotherapy or ablation.
The decision depends on the number and location of lesions, overall disease distribution, lung function and the likelihood that all clinically relevant disease can be controlled.
SYSTEMIC TREATMENTS FOR METASTATIC COLORECTAL CANCER
Systemic treatments circulate through the body and are particularly important when cancer cannot be adequately managed with local treatments alone.
Chemotherapy
Common regimens include FOLFOX, FOLFIRI, CAPOX and, for selected patients, FOLFOXIRI.
These regimens use different combinations of fluoropyrimidines, oxaliplatin and irinotecan.
Targeted therapy
Targeted drugs may be added depending on molecular findings and clinical circumstances.
Examples include:
- Bevacizumab and other anti-angiogenic approaches
- Cetuximab or panitumumab for appropriately selected RAS wild-type tumors
- BRAF-directed combinations for eligible BRAF V600E-mutated disease
- HER2-directed treatment for selected HER2-positive cancers
- Other mutation-specific treatments when approved and clinically appropriate
Immunotherapy
Checkpoint inhibitors can be particularly effective in some colorectal cancers with deficient mismatch repair (dMMR) or high microsatellite instability (MSI-H).
For most microsatellite-stable colorectal cancers, conventional checkpoint inhibitors alone have not demonstrated the same level of benefit.
That is why molecular testing is essential before assuming immunotherapy is appropriate.
THE BIOMARKERS THAT CAN CHANGE TREATMENT
Biomarkers help oncologists understand the biology of a tumor and select treatments more precisely.
Identifies mismatch repair deficiency or microsatellite instability. These findings can predict sensitivity to certain immunotherapies and may indicate a need for genetic evaluation for Lynch syndrome.
RAS mutations are important when deciding whether anti-EGFR therapies such as cetuximab or panitumumab are likely to help.
A clinically important molecular alteration associated with distinct tumor biology and specific targeted treatment options.
HER2 amplification can identify a subgroup of metastatic colorectal cancers that may benefit from HER2-directed treatment.
Rare alterations, including certain gene fusions and specific mutations, may open additional targeted treatment options or clinical-trial opportunities.
Not every biomarker is relevant to every patient at every stage. Testing should be matched to the clinical setting and the decisions it can inform.
CEA: WHAT CAN THIS BLOOD TEST REALLY TELL YOU?
CEA is a tumor-associated marker often used during colorectal cancer follow-up.
It can help identify possible recurrence or monitor treatment response in some patients.
However, some colorectal cancers produce little or no CEA, even when disease is present.
A normal CEA result does not rule out active cancer.
Likewise, an elevated CEA result is not proof of recurrence because noncancerous conditions can also affect the level.
CEA is most useful when interpreted alongside imaging, clinical findings and trends over time.
CTDNA AND LIQUID BIOPSY
Circulating tumor DNA, or ctDNA, consists of fragments of tumor-derived DNA that may be detectable in blood.
After surgery or other treatment, ctDNA testing may help identify molecular residual disease and estimate recurrence risk.
In metastatic disease, liquid biopsy can also help detect molecular alterations and treatment resistance.
But a negative ctDNA result does not prove that no microscopic disease remains.
A test may accurately identify higher recurrence risk without proving that changing treatment based on the result improves survival.
Routine use of ctDNA to direct every treatment decision is not established across all colorectal cancer settings.
WHAT DOES NED MEAN?
NED means No Evidence of Disease.
It describes a situation in which current examinations and tests do not identify detectable cancer.
NED is an important and encouraging clinical status, but it does not guarantee that microscopic cancer cells are absent.
The same distinction applies after apparently complete surgery or ablation.
Modern imaging can detect many small lesions, but no scan can reliably exclude every microscopic cancer cell.
FOLLOW-UP AFTER COLORECTAL CANCER TREATMENT
Follow-up aims to detect potentially treatable recurrence, monitor treatment effects and support long-term health.
Depending on stage and treatment history, follow-up may include:
- Clinical assessments
- CEA blood tests when appropriate
- CT or other imaging at planned intervals
- Colonoscopy surveillance
- Monitoring neuropathy, bowel function and other treatment effects
- Nutrition, physical activity and psychosocial support
The schedule is individualized according to recurrence risk, previous treatments and relevant guidelines.
More frequent scans are not automatically better. Follow-up should balance potential benefits against radiation exposure, false alarms, anxiety and unnecessary procedures.
WHAT DETERMINES THE RISK OF RECURRENCE?
Recurrence risk is influenced by multiple factors, including:
- Original tumor stage
- Number of involved lymph nodes
- Tumor grade and pathological risk features
- Surgical margin status
- Molecular characteristics
- Presence and extent of metastatic disease
- Response to treatment
- Whether all detectable disease was completely treated
No single factor can accurately predict an individual patient’s future.
Population statistics are useful for understanding patterns but cannot determine exactly what will happen to one person.
COMMON MISUNDERSTANDINGS
“Normal CEA means there is no cancer.”
False. CEA has important sensitivity limitations.
“Stage IV always means treatment cannot aim for cure.”
False. Selected patients with limited metastatic disease may be candidates for potentially curative treatment.
“A clear scan proves every cancer cell is gone.”
False. Microscopic disease may remain below imaging detection limits.
“Every patient needs the same chemotherapy.”
False. Treatment depends on stage, molecular biology and patient-specific factors.
“Immunotherapy works for all colorectal cancers.”
False. Benefit is strongly influenced by tumor biology, especially MSI/MMR status.
LIVING WITH AND AFTER COLORECTAL CANCER
Medical treatment is only one part of cancer care.
Patients may also need help with nutrition, bowel changes, fatigue, neuropathy, emotional distress, sexual health and returning to everyday activities.
After colon or rectal surgery, bowel habits may change. Some patients experience more frequent stools, urgency or altered digestion.
These symptoms should be discussed with the medical team, especially when they interfere with nutrition, hydration or quality of life.
Physical activity adapted to individual ability, adequate nutrition, smoking cessation and attention to general health can support recovery.
There is no supplement or special diet proven to replace established colorectal cancer treatment.
QUESTIONS TO ASK YOUR ONCOLOGY TEAM
- What is my exact TNM stage?
- What does my pathology report say about lymph nodes and margins?
- Is the treatment plan intended to cure the cancer or control it?
- Have MSI/MMR and other relevant biomarkers been tested?
- Would additional imaging change the treatment plan?
- If metastases are present, could surgery or ablation treat all known disease?
- Should my case be reviewed by a specialized multidisciplinary team?
- What benefits and side effects should I expect from treatment?
- Would CEA or ctDNA testing be useful in my situation?
- What is the follow-up plan after treatment?
THE BOTTOM LINE
Colorectal cancer is treatable at every stage, but the goals and available treatments differ substantially.
Early-stage disease is often managed with surgery, sometimes followed by chemotherapy. Locally advanced rectal cancer may require treatment before surgery. Metastatic disease usually requires systemic treatment, but selected patients with limited metastases may benefit from potentially curative local approaches.
The most useful treatment decisions come from combining accurate staging, pathology, molecular testing, specialist assessment and the patient’s own priorities.
RELATED CANCERSNOOP ARTICLES
SOURCES
National Cancer Institute
Rectal Cancer Treatment (PDQ®) — Health Professional Version
View source →National Cancer Institute
Do Frequent Follow-Up Tests Help Colorectal Cancer Survivors?
View source →European Journal of Cancer Care — 2021
Diagnostic accuracy of follow-up tests for detecting colorectal cancer recurrences: A systematic review and meta-analysis
PMID: 33704843 | DOI: 10.1111/ecc.13432
View study →LAST REVIEWED
October 16, 2026
Comments (0)